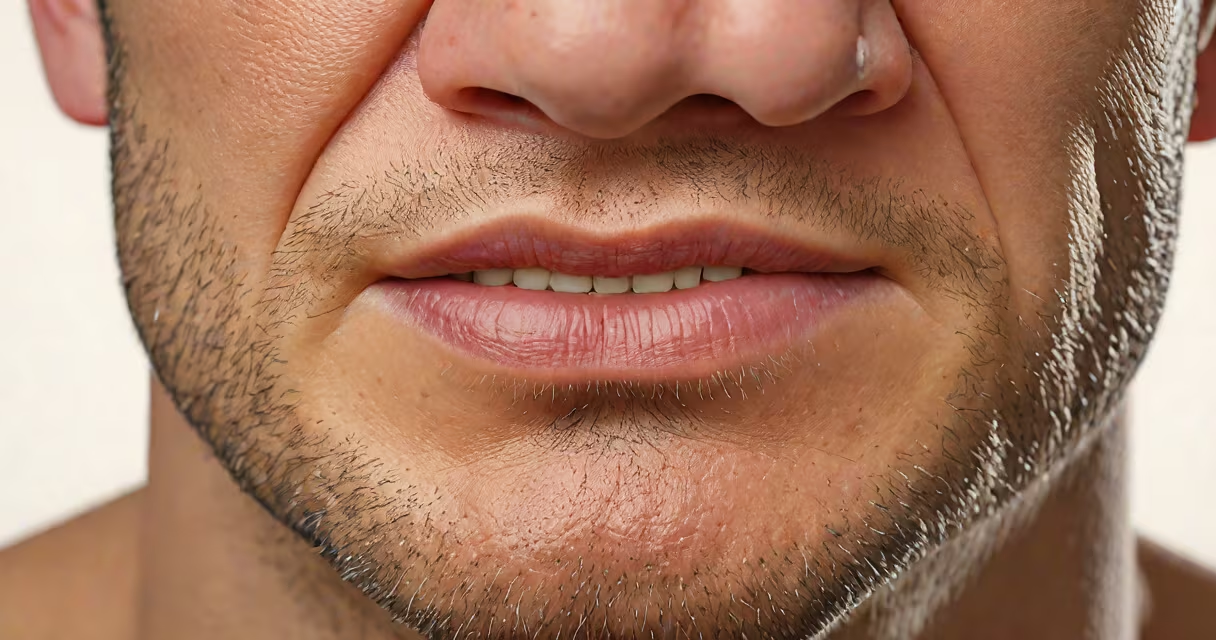
A tetanus infection causes severe muscle stiffness and painful spasms, beginning with tight jaw muscles (lockjaw) and progressing to full-body rigidity. It results from a toxin produced by Clostridium tetani bacteria entering a wound, not from direct contact with soil or rust.
Tetanus is not contagious. The bacteria thrive in low-oxygen environments like deep puncture wounds, burns, or contaminated injection sites. Once inside, they release tetanospasmin, a neurotoxin that blocks inhibitory signals in the spinal cord, leading to uncontrolled muscle contractions.
Early signs include difficulty swallowing, stiffness in the neck and jaw, and mild fever. As the disease advances, patients develop opisthotonus-arching of the back with the head thrown backward-and sustained muscle spasms triggered by light, sound, or touch. These episodes can last minutes and cause fractures or respiratory failure.
The most recognizable sign is trismus-the inability to open the mouth due to jaw muscle spasm. This gives the face a fixed, grimacing expression. The tongue may protrude between tightly closed teeth, and the patient cannot speak.
Spasms spread downward. After jaw stiffness, neck stiffness appears, followed by abdominal rigidity. The abdomen becomes board-hard. Back arching (opisthotonus) occurs when the back muscles contract violently, lifting the head and feet off the bed.
Facial muscles may twitch uncontrollably. A patient's face can appear frozen, with raised eyebrows and flared nostrils. Skin may turn pale or cyanotic during spasms due to interrupted breathing.
Tetanus has three clinical forms:
Risk increases with injuries involving dirt, feces, or metal fragments. Deep wounds from nails, animal bites, or surgical procedures carry higher risk. People who haven't had a tetanus booster in 10 years are vulnerable.
According to the World Health Organization, neonatal tetanus caused over 100,000 deaths annually before widespread vaccination. Today, global cases have dropped below 50,000 per year, mostly in low-resource regions.
Tetanus is often mistaken for stroke, rabies, or drug withdrawal. But unlike stroke, which causes sudden weakness on one side, tetanus affects muscles symmetrically. Unlike rabies, which includes hydrophobia and confusion, tetanus lacks fever or altered mental status early on.
Another common error: thinking rust causes tetanus. Rust itself doesn't harbor the bacteria. However, rusty objects often carry soil, which contains Clostridium tetani spores. The myth persists because rusty nails frequently cause deep puncture wounds.
One non-obvious fact: tetanus can occur without a visible wound. A minor scratch or insect bite can introduce spores if the skin barrier is compromised. In rare cases, it develops after dental surgery or bowel perforation.
In 2018, a 52-year-old farmer in rural India stepped on a nail while working barefoot. He ignored the small wound. Seven days later, he couldn't open his mouth. His jaw locked. By day nine, he experienced violent back arching during a loud noise. He was admitted to a hospital with suspected stroke but tested positive for tetanus via clinical signs and history.
He received human tetanus immune globulin (TIG), antibiotics, and muscle relaxants. He spent 21 days in ICU, requiring intubation. Recovery took over six months. He had no prior tetanus vaccination.
This case illustrates how quickly tetanus can progress and why prevention matters. The WHO recommends a primary series of five doses of tetanus toxoid vaccine, followed by boosters every 10 years.
Diagnosis is clinical-not based on lab tests. There is no specific test for tetanus. Doctors rely on symptoms, history of injury, and absence of other neurological conditions.
Treatment includes:
Without treatment, mortality exceeds 30%. With intensive care, survival improves but recovery is slow and painful.
Vaccination prevents tetanus. The DTaP vaccine (diphtheria, tetanus, acellular pertussis) is given to children at 2, 4, 6, and 15-18 months, and again at 4-6 years. Adults need a Tdap booster every 10 years.
After any deep or dirty wound, especially if the last tetanus shot was over 5 years ago, a booster is recommended. The CDC states that even a clean cut can lead to tetanus if the person hasn't been vaccinated.
One personal observation: during a field visit to a clinic in Kenya, I saw a child with generalized tetanus. The mother had delayed care due to fear of hospitals. The child died within 48 hours. Vaccination prevented this outcome in nearly all other children in the village.
Understanding what a tetanus infection looks like saves lives. Recognizing early signs-jaw stiffness, difficulty swallowing-can prompt urgent care. Preventing it through vaccination remains the most effective strategy.